NCLEX Prioritization and Delegation Framework
Use five decision filters to solve NCLEX prioritization and delegation questions, avoid tempting distractors, and measure progress with focused practice.
NCLEX prioritization and delegation questions are difficult because several answer choices may describe reasonable nursing actions. The real task is narrower: identify what must happen first, what the RN must retain, and what can safely be assigned or delegated under the conditions described.
A practical framework for NCLEX prioritization and delegation should therefore do more than repeat “ABCs” or list staff roles. It should help you compare competing risks through five filters: **stability, immediacy of harm, scope of practice, predictability, and the need for nursing judgment**.
The current NCLEX test plans specifically include assignment, delegation, supervision, clinical judgment, personnel competency, and the rights of delegation. The framework below is a study tool for applying those concepts consistently—not an official NCLEX scoring algorithm.
Why Reasonable Answers Become Wrong Answers
Most prioritization errors are comparison errors rather than knowledge errors. You recognize that every client needs care, but you select an important intervention instead of the most urgent one. In delegation questions, you may know that assistive personnel can obtain routine measurements but overlook that this particular measurement requires interpretation or immediate follow-up.
Before choosing an answer, clarify the decision the item is testing:
- **Priority:** Which client, finding, or intervention requires attention first?
- **Assignment:** Which team member should receive responsibility for care within that person’s established role?
- **Delegation:** Which specific activity can be transferred safely while the licensed nurse retains appropriate accountability and supervision?
- **Follow-up:** Which finding requires the RN to reassess, intervene, or clarify immediately?
Do not solve an assignment question as though it were only asking who is technically capable of performing a task. The client’s condition and the amount of judgment required matter just as much as the task itself.
The Five-Filter Framework for NCLEX Prioritization and Delegation
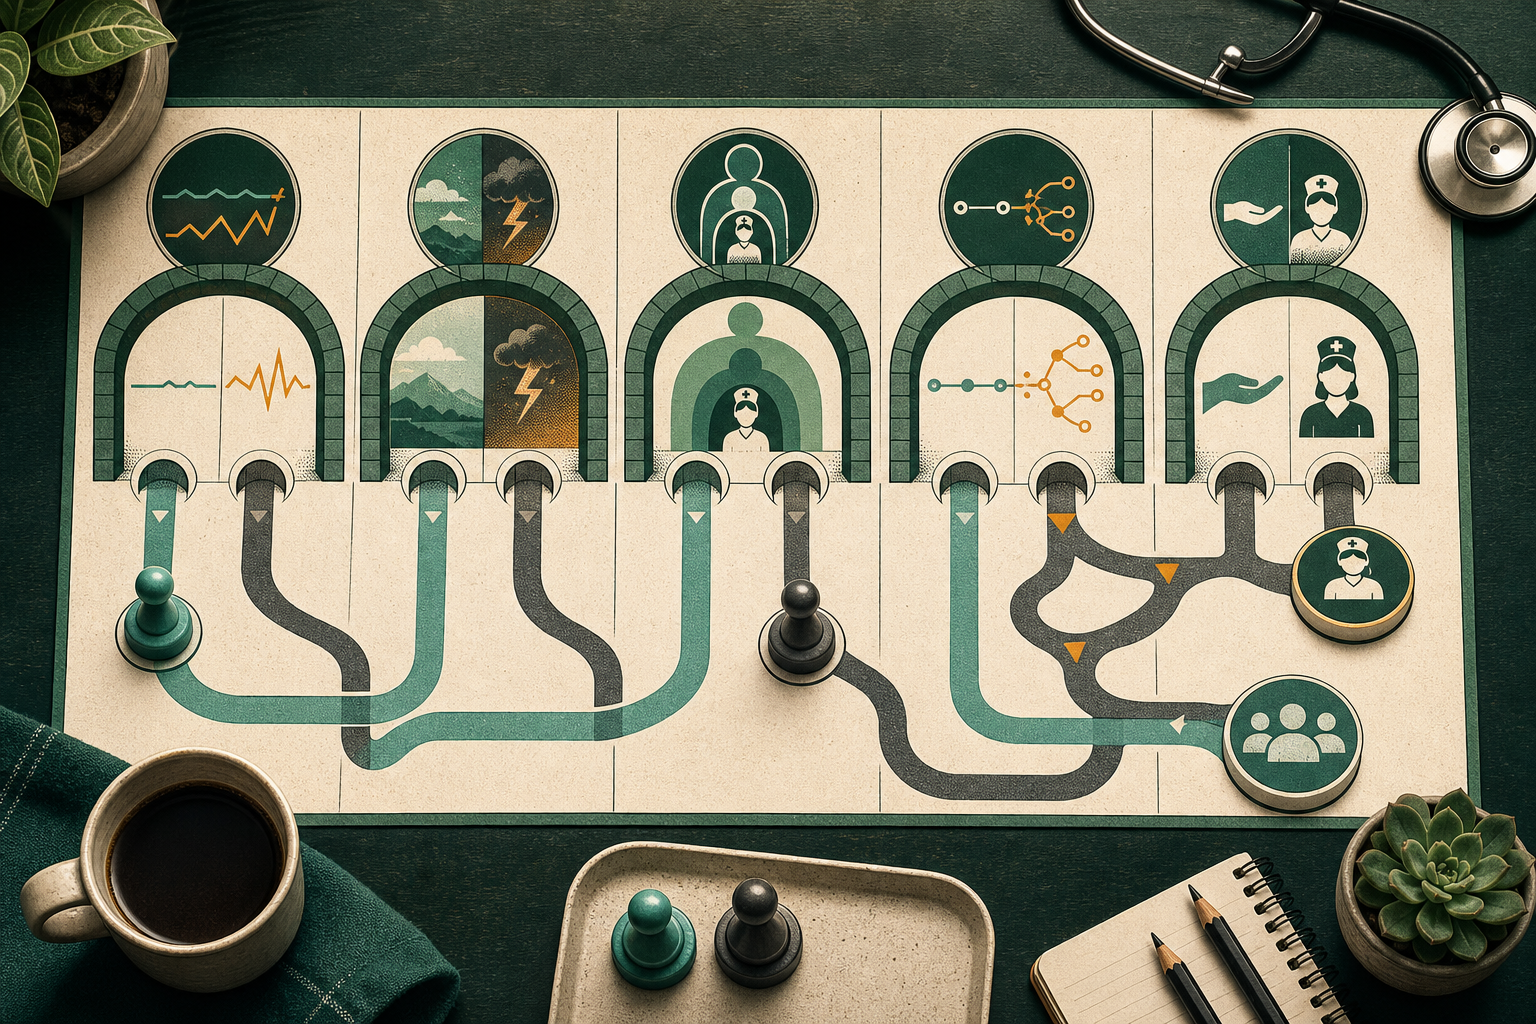
Move each plausible answer through the following filters. You may not need all five every time, but using the same sequence reduces impulsive decisions.
1. Stability: Is the Client’s Condition Changing?
A stable client has an expected, reasonably controlled clinical course. An unstable client has a new, worsening, unexpected, or insufficiently assessed condition.
Look for instability cues such as:
- New confusion, restlessness, or decreased responsiveness
- Sudden respiratory difficulty or changing oxygen needs
- Unexpected bleeding or rapidly changing vital signs
- New chest pain, weakness, or neurologic findings
- A significant change from the client’s baseline
- Failure to respond as expected to treatment
Do not equate “chronic” with stable or “postoperative” with unstable. A client with chronic lung disease and baseline oxygen saturation documented at 90% may be more stable than a previously well client whose saturation has abruptly fallen to 90%.
**Practical rule:** Compare each finding with the client’s baseline, expected course, and recent trend.
2. Immediacy of Harm: What Happens If Care Is Delayed?
Ask what could happen during the next few minutes—not merely what could become a problem eventually.
Conditions involving a threatened airway, severe breathing difficulty, impaired circulation, rapidly changing neurologic status, or active safety danger usually outrank discomfort, routine teaching, and expected findings. However, do not select an answer simply because it contains an airway-related word. The threat must be supported by the scenario.
A client requesting prescribed pain medication needs care. A client with new stridor may suffer catastrophic harm if care is delayed. The second client is the priority because the time-to-harm is much shorter.
**Practical rule:** When two choices are important, prioritize the one associated with the fastest serious deterioration.
3. Scope of Practice: Is This Person Authorized and Prepared?
In delegation questions, eliminate any option that clearly falls outside the team member’s role as described in the item. Then consider competency, setting, organizational policy, and required supervision.
Scope rules vary by jurisdiction and workplace. The American Nurses Association’s delegation guidance emphasizes the right task, circumstance, person, direction or communication, and supervision or evaluation. For exam purposes, use the personnel information provided in the question rather than assuming that every facility follows identical rules.
**Practical rule:** Scope is a hard boundary, not a reason to ignore the other filters. A task can be generally permitted yet inappropriate for a particular unstable client.
4. Predictability: Is the Task and Outcome Routine?
Delegation becomes safer when the client is stable, the activity is standardized, and the expected result is predictable. Examples may include hygiene, routine intake and output measurement, repositioning, or ambulation for a stable client after the plan has been established.
Predictability falls when:
- The client has not been adequately assessed
- The response to the activity is uncertain
- The task may require modification during performance
- Abnormal data are likely to require immediate interpretation
- Complications are developing or reasonably suspected
For example, assisting a stable client with routine ambulation may be appropriate for assistive personnel. The first ambulation of a client who recently experienced syncope presents a different circumstance because assessment and clinical decision-making are central to safe care.
5. Nursing Judgment: Must Someone Assess, Interpret, Teach, or Evaluate?
The RN should retain responsibilities that depend on nursing judgment. Common NCLEX signals include:
- Performing an initial or focused assessment of a new problem
- Interpreting clinical findings or trends
- Developing or changing the plan of care
- Providing initial teaching that requires assessment of learning needs
- Evaluating a client’s response to an intervention
- Managing an unstable or unpredictable condition
- Deciding whether escalation or provider notification is required
A team member may collect data, but the RN determines what the data mean. For example, assistive personnel might obtain a routine blood pressure on a stable client. The RN must evaluate an unexpected result and decide what happens next.
| Question cue | Stronger decision filter | Ask yourself | |---|---|---| | “Which client should the nurse see first?” | Immediacy and stability | Who could suffer serious harm soonest? | | “Which task can be delegated?” | Scope, predictability, and judgment | Is it authorized, routine, and unlikely to require interpretation? | | “Which assignment should the charge nurse change?” | Stability and staff capability | Has an unstable or complex client been assigned inappropriately? | | “Which finding requires follow-up?” | Change and potential harm | Is this new, unexpected, or dangerous if ignored? | | “Which action should the nurse take first?” | Immediate safety and assessment needs | Is enough information available to intervene safely? |
A 45-Second Workflow for Each Question
Use four passes instead of repeatedly rereading the full item.
Pass 1: Name the Decision
Translate the stem into a short instruction: “Find the least stable client,” “protect the RN judgment task,” or “identify the safest routine task.” This prevents a true but irrelevant answer from attracting you.
Pass 2: Mark Change and Time-to-Harm
Identify words showing what is new, worsening, unexpected, or immediate. If the item presents four clients, compare trends rather than diagnoses alone.
Pass 3: Protect Nursing Judgment
For delegation, ask whether the task includes assessment, interpretation, planning, initial teaching, or evaluation. If it does, keep it with the RN unless the item provides a specific licensed role and authorized responsibility that changes the analysis.
Pass 4: Test the Final Choice Against the Stem
Finish this sentence: “This answer is best because…” Your explanation should refer to the scenario, not a slogan.
A strong rationale might be: “This client has a new airway finding and the shortest time-to-serious harm.” A weak rationale is: “Airway always comes first.” The second statement ignores whether a genuine airway threat exists.
Applying the Framework to Common Delegation Choices
Use role patterns as starting points, not absolute rules.
| Team member | Common exam-pattern responsibilities | Responsibilities usually retained by the RN | |---|---|---| | RN | Unstable clients, assessment, care planning, complex teaching, evaluation, clinical decisions | All activities requiring RN-level judgment | | LPN/VN | Care for stable clients, routine procedures, reinforcing established teaching, and other authorized activities | Initial assessment of a new problem, independent care planning, and management of unpredictable instability | | Assistive personnel | Routine, standardized care for stable clients; activities of daily living; collection of specified data | Assessment, interpretation, teaching, evaluation, and decisions about changing care |
Always read for exceptions. If the item states that a team member lacks competency, is unfamiliar with equipment, or has not been validated for a task, that detail overrides a general role pattern.
Also separate **doing** from **deciding**. A team member may perform an activity, while the RN remains responsible for determining that it is appropriate, communicating expectations, supervising as needed, and evaluating the outcome.
How to Review Tempting Distractors
Reviewing only the correct answer leaves the most valuable question unanswered: Why did the distractor feel safer or more familiar?
After each missed or uncertain question, complete a brief “distractor autopsy”:
- **Record your choice and the correct choice.** Do not rely on memory.
- **Name the attraction.** Was your answer familiar, technically true, dramatic, or associated with a memorized rule?
- **Identify the failed filter.** Did you miss instability, underestimate time-to-harm, cross scope, assume predictability, or delegate judgment?
- **Rewrite the deciding fact.** Use one sentence: “New confusion made this client less stable than the client with expected postoperative pain.”
- **Create a future trigger.** Example: “When two findings are abnormal, compare which one is new and which can cause harm sooner.”
Classify tempting distractors into recurring types:
- **True but not first:** The action is appropriate after the immediate threat is addressed.
- **Severe-sounding but expected:** The diagnosis is serious, but the finding is baseline or controlled.
- **Task-focused but client-blind:** The activity is normally delegable, but this client is unstable.
- **Data collection without evaluation:** The option gathers information but fails to address a dangerous finding already present.
- **Scope-correct but competency-incorrect:** The role may perform the task generally, but the individual or circumstance is unsuitable.
- **Automatic-rule answer:** The choice applies ABCs, Maslow, or another hierarchy without considering the actual cues.
This review method uses active retrieval rather than passive rereading. In health-professions education, research on repeated retrieval practice has found benefits for long-term retention and transfer compared with repeated review. The evidence supports practicing decisions and retrieving rationales; the specific five-filter worksheet is a practical recommendation designed for NCLEX-style review.
A Seven-Day Focused Practice Schedule
Use short mixed sets so you must decide which filter applies instead of being told the question category in advance.
| Day | Practice assignment | Review target | |---|---|---| | 1 | 15 untimed prioritization questions | Identify stability and immediate harm cues | | 2 | 15 untimed delegation questions | Separate routine tasks from nursing judgment | | 3 | 20 mixed questions | Name the primary filter before viewing the rationale | | 4 | Rework every missed or uncertain question without notes | Test whether your reasoning changed | | 5 | 20 mixed questions with a reasonable time limit | Use the four-pass workflow without rushing | | 6 | Review 10 tempting distractors from your log | Identify repeated error patterns | | 7 | Complete a 25-question mixed checkpoint | Measure accuracy, confidence, and reasoning consistency |
Do not respond to a low score by immediately doubling question volume. First determine whether the problem is content knowledge, missed cues, role confusion, or inconsistent decision order.
Progress Checkpoints That Measure Reasoning
Track more than percentage correct. At the end of each week, calculate or estimate:
- **First-pass accuracy:** Questions answered correctly without changing the response
- **Uncertain-but-correct rate:** Correct answers chosen with low confidence, which still need review
- **Filter identification:** Whether you can name the deciding filter before reading the rationale
- **Repeated-error count:** How often the same mistake appears in your distractor log
- **Rationale quality:** Whether you can explain the correct answer using a client-specific fact
A useful progression is qualitative as well as numerical:
- **Recognition:** You can identify stability, harm, scope, predictability, and judgment after reading a rationale.
- **Application:** You can select the relevant filter while answering an untimed question.
- **Comparison:** You can explain why the best choice outranks a tempting alternative.
- **Automaticity:** You can apply the workflow efficiently in mixed, timed practice without reverting to slogans.
Failure Modes That Undermine the Framework
**Treating every abnormal finding as equally urgent.** Compare the finding with baseline, expected course, and time-to-harm.
**Using ABCs without reading the evidence.** A stable oxygen requirement does not automatically outrank a new neurologic change.
**Delegating by task name alone.** “Obtain vital signs” sounds routine until the client is newly unstable or the measurement will drive an immediate clinical decision.
**Assuming all LPN/VNs or assistive personnel have identical authority.** Follow the scenario’s stated scope, competency, and setting. Do not invent permissions that are not provided.
**Adding facts to rescue an answer.** Judge the information given. If an option becomes correct only after you assume extra assessment findings, policies, or qualifications, it is probably not the best answer.
**Reviewing only content categories.** If your recurring mistake is selecting “important but not first,” another content lecture may not fix it. Practice ranking urgency and explaining why one option outranks another.
Final Takeaways
- Compare clients by **change, stability, and time-to-harm**, not diagnosis labels alone.
- Delegate only when scope, competency, circumstances, and predictability support the decision.
- Retain assessment, interpretation, initial teaching, planning, and evaluation when they require RN judgment.
- Review tempting distractors by naming the exact filter they fail.
- Measure progress by reasoning consistency as well as question-set accuracy.
Build these decisions into a repeatable habit with Explore focused exam preparation at Core Test Prep.